
⏱ 18 min read
Hospital 366 Days · Case No. 12
The hospital’s year does not end at 365. It runs to 366, and keeps going.
Call him Walt. Age, occupation, location, and any potentially identifying details have been changed. The clinical pattern is a composite reconstructed from cases that American emergency rooms see repeatedly over a year, and it does not represent any specific patient.
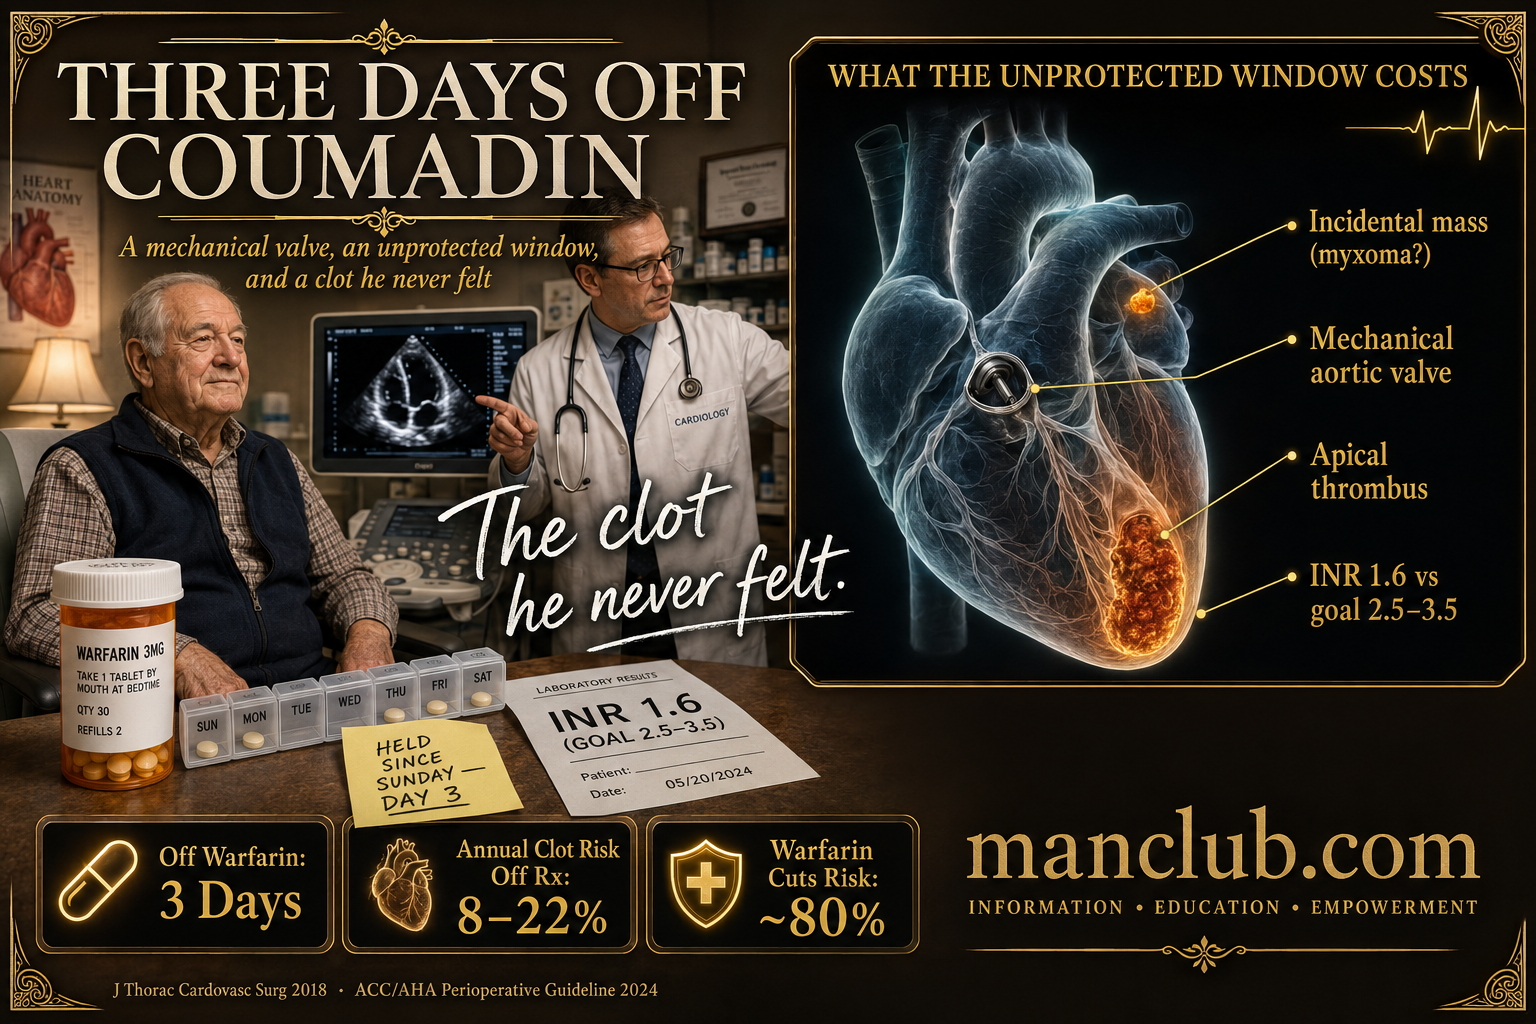
A man with a mechanical heart valve lives between two risks every single day. Take enough warfarin and there is a bleeding risk. Take too little and a clot can form on the valve itself. Without anticoagulation, a mechanical valve carries an annual thromboembolic risk of 8% to 22%. Warfarin lowers that risk by about 80%. (JTCVS 2018) For a mechanical valve patient, warfarin is not optional. It is a lifelong requirement.
The trouble is that this requirement conflicts with other medical needs. Stopping warfarin before surgery or any procedure with a bleeding risk is standard, because the drug raises bleeding during the procedure itself. For those few days, the valve is unprotected again. This case is about what can happen during that window, and about a second finding nobody was looking for.
This patient had a minor procedure scheduled by another specialist. He was told to hold his warfarin for a few days beforehand, and he did exactly that. No injectable blood thinner was arranged to cover the gap. He had no symptoms. No shortness of breath, no dizziness, no lightheadedness.
During those days off the drug, he had a routine heart ultrasound on the calendar, the kind a mechanical valve patient gets periodically to monitor the valve. The scan found a blood clot at the tip of his left ventricle. The procedure was canceled, and he was sent to the emergency department that same afternoon. He still felt fine.
This is not the path most 76-year-old men are on. It is what stopping warfarin before surgery can look like in a mechanical valve patient when the gap is not bridged. Below are the days that brought him in, and the second thing the hospital found while looking at the first.
What Appeared on the Screen
Walt was 76 and retired. His wife drove him to the cardiology office that Wednesday for a scheduled valve check. He felt no different from usual.
His history was long. A mechanical aortic valve, placed several years earlier. Longstanding atrial fibrillation. A permanent pacemaker set in a dual-chamber rate-responsive mode. Chronic obstructive pulmonary disease. He had smoked for decades before quitting in his sixties, the history behind his COPD. He had no regular primary care physician. A cardiologist managed his heart and his valve, and other care was spread across specialists who saw him for one thing at a time.
His INR goal for the mechanical aortic valve was 2.5 to 3.5. That range is higher than the 2.0 to 3.0 used for ordinary atrial fibrillation, because a mechanical valve clots more easily than a native one. On the day of the visit, his INR was 1.6. He had been off warfarin since Sunday to prepare for the upcoming procedure.
The ultrasound technician moved the probe across his chest. On the screen, at the apex of the left ventricle, was a thrombus. A clot, in the very tip of the heart’s main pumping chamber. Walt felt nothing and saw only a gray image he could not read. The cardiologist canceled the procedure and arranged transfer to the emergency department. The clot, not the original procedure, was now the problem.
The reason this mattered so much is simple. A clot at the apex of the left ventricle can break loose, travel up the aorta, and lodge in an artery feeding the brain. That is a stroke. Walt had no symptoms, which is exactly why the finding was unsettling. The danger had been building silently while he followed his instructions.
Three Days Off Coumadin
Sunday (Day 0). Walt took his last warfarin dose in the evening. The instructions for the upcoming procedure said to hold the drug for several days. No instruction to bridge with an injectable blood thinner came from either the specialist doing the procedure or the cardiology side. He simply stopped.
Monday (Day 1). No symptoms. He went through an ordinary day. His mild ankle swelling was at its usual level.
Tuesday (Day 2). Still no symptoms. He took his other medications as usual: the statin, the beta blocker, the diuretic at night, the blood pressure pill. Just not the warfarin.
Wednesday (Day 3). His wife drove him to the cardiology office for the scheduled valve check. The routine heart ultrasound showed the apical thrombus. The procedure was canceled. He arrived at the emergency department that afternoon, still without a single symptom he could point to.
Three days without the drug had dropped his INR from his usual therapeutic range to 1.6. That is what stopping warfarin before surgery does. The INR falls over days, the valve loses its protection, and the patient feels no difference.
Stopping Warfarin Before Surgery: What the ED Workup Found
Triage vitals were stable. Blood pressure 132/78, heart rate 68 (paced and beta-blocked), respiratory rate 16, oxygen saturation 95% on room air, no fever. He denied shortness of breath, chest pain, dizziness, and lightheadedness.
Lab results: INR 1.6, still well below the 2.5 to 3.5 goal for a mechanical valve. Troponin was right at the reference limit and not rising. Pro-BNP was about 690 pg/mL. CK-MB was within normal limits. Creatinine was mildly elevated at around 1.2 and improving, with a BUN near 28. Hemoglobin A1c was 6.0.
Imaging: the chest X-ray showed stable sternotomy wires from the prior valve surgery and a two-lead pacing device, with no acute findings. The routine ultrasound had already shown the apical clot. A transesophageal echocardiogram, the sharper view taken through the esophagus, was then performed to define the clot and look for anything else.
The transesophageal study confirmed the apical thrombus. It also found something nobody had been looking for: a small, separate mass inside the heart, with an appearance suggesting either a myxoma or a fibroma. A clot is treated with blood thinner. A cardiac mass is a different problem, one that usually goes to a cardiothoracic surgeon. The single test done to characterize one finding had uncovered a second.
The orders followed quickly. An intravenous heparin drip was started on protocol, with a weight-based bolus, a maintenance infusion, and aPTT checks every six hours. Warfarin was restarted at 10 mg by mouth that day. INR was to be checked daily. He was kept from eating or drinking in case a procedure was needed. Transfer to a regional cardiothoracic center was arranged for surgical evaluation of the mass.
One detail from the heparin drip is worth holding onto. An early aPTT came back at about 165 seconds, far above the target range. That is over-anticoagulation, which carries the bleeding risk the warfarin pause had been meant to avoid. The dose was cut and the next value came down to about 58. The clot and the bleeding risk were never far apart at any point in this admission.
Plain-Language Reference
| Term | What It Means in Plain Language |
|---|---|
| Aortic stenosis | A narrowing of the aortic valve that blocks blood leaving the heart. The most common reason an older adult needs a valve replacement. |
| Mechanical heart valve | An artificial valve made of durable synthetic material. It can last a lifetime, but its surface activates blood clotting, so it requires lifelong blood thinner. |
| Warfarin (Coumadin) | The blood thinner that keeps clots from forming on the valve. Same drug under two names. Its strength is measured by the INR. |
| INR | A blood test that shows how thinned the blood is. Higher means more anticoagulated. A mechanical aortic valve usually targets 2.5 to 3.5. |
| Bridging anticoagulation | Using a fast-acting injectable blood thinner (heparin) to cover the unprotected gap when warfarin is paused for a procedure. |
| Apical thrombus | A blood clot at the tip (apex) of the left ventricle, the heart’s main pumping chamber. A piece can break off and travel to the brain, causing a stroke. |
| TTE and TEE | TTE is a heart ultrasound through the chest wall. TEE is taken through the esophagus and gives a sharper view of valves, clots, and masses. |
| Cardiac myxoma | The most common benign primary tumor of the heart. Usually harmless in itself, but fragments can break off and embolize, so it is typically removed surgically. |
| aPTT (PTT) | A blood test that measures heparin’s effect. A value far above target means the blood is over-thinned, which raises bleeding risk. |
| DDDR pacemaker | A permanent pacemaker that paces and senses both the upper and lower chambers and adjusts the heart rate to the body’s activity. |
| Clinical Marker | Patient’s Presentation | Significance & Reference Literature |
|---|---|---|
| Mechanical Valve, Subtherapeutic INR | INR 1.6 (goal 2.5 to 3.5) | A mechanical valve without therapeutic anticoagulation carries an 8% to 22% annual thromboembolic risk; warfarin reduces this by about 80% (JTCVS 2018). |
| Apical Left Ventricular Thrombus | Found on routine echo | A dislodged fragment can embolize to the brain. Mechanical valve thromboembolism carries roughly 20% mortality and 40% major disability (JTCVS 2018). |
| Three-Day Warfarin Hold | Stopped Sunday, INR 1.6 by Day 3 | INR falls over days, not hours, and rebuilds over days. The unprotected window is when valve and chamber thrombus tends to form. |
| Bridging Not Performed | Mechanical aortic valve + AFib | 2024 AHA/ACC: bridging is reasonable (Class 2a) for high thrombotic risk including high-risk AFib; routine bridging can harm through bleeding (Class 3) (ACC 2024). |
| Supratherapeutic aPTT on Heparin | aPTT ~165, corrected to ~58 | Bridging itself raises perioperative bleeding by 4% to 8% (Balaji 2024). The narrow target between clot and bleed is the whole difficulty. |
| Incidental Cardiac Mass | Small mass on TEE | Myxoma is the most common primary cardiac tumor, about 0.5 to 1 per million people per year. A meaningful share embolize, so removal is standard (Cardiothoracic Surgeon 2024). |
Three days off one pill, a clot in the heart’s tip, and a second mass nobody was looking for.
From the Reviewer · Eleanor Hayes, M.D.
(A) A danger that was found, not felt
The striking thing in cases like this is that the patient feels nothing. A clot at the apex of the left ventricle does not announce itself. There is no pain, no breathlessness, no warning. It sits there until a piece breaks off, and then the first symptom is a stroke. What caught it here was a routine ultrasound, the kind of study that can feel like a formality. In a mechanical valve patient who has paused anticoagulation, that study is not a formality. It is the only thing standing between a silent clot and an event.
(B) Why a heart valve gets replaced in the first place
Most readers meet a valve patient without ever hearing what sent him to the operating room. For the aortic valve, the usual answer is aortic stenosis, a narrowing of the valve that blocks blood leaving the heart. It affects roughly 3% of people over 65, and in older adults the cause is usually degenerative calcium buildup on the valve over many years. (AAFP) The disease is quiet for a long time. There is often a latent period of 10 to 20 years with no symptoms at all, while the heart muscle thickens to push blood through the narrowing opening. (Medscape) Then the compensation runs out, and three classic symptoms tend to appear: chest pain on exertion, fainting, and breathlessness. Diagnosis is usually made with an echocardiogram, the same kind of ultrasound that later caught this man’s clot.
(C) Once symptoms begin, replacement stops being optional
This is the part patients are often surprised by. While aortic stenosis is silent, watchful waiting is reasonable. Once those classic symptoms appear, the outlook changes sharply. Average survival without valve replacement falls to about two to three years after symptoms begin. (AAFP) No medication slows or reverses the narrowing. Replacing the valve, either by open surgery or by a catheter-delivered valve, is the only treatment that changes that outcome. (Merck Manual) So when a patient like this one was told he needed his aortic valve replaced, it was not an elective tune-up. It was what gave him the years he has lived since.
(D) Mechanical or tissue, and how long each lasts
When the valve is replaced, there are two broad choices. A mechanical valve is made of durable synthetic material and can last the rest of a patient’s life without wearing out. A tissue valve, made from treated animal or human tissue, usually does not require lifelong blood thinner, but it wears down in roughly 10 to 20 years and may need to be replaced again. (Harvard Health) Because of that durability difference, guidelines generally favor mechanical valves under age 50 and tissue valves over age 70, with the middle years a genuine judgment call. (Canadian Journal of Cardiology 2020) A patient may receive a mechanical valve to avoid a second open operation, or because his atrial fibrillation already commits him to lifelong warfarin. When a patient is going to be on warfarin anyway, the main downside of the mechanical valve loses much of its weight.
(E) Life after a valve replacement
The encouraging part is what comes after. Once the valve is replaced and the patient recovers, symptoms ease and survival moves back toward what would be expected for someone the same age without valve disease. (JACC 2018) Day-to-day life is close to normal. For a mechanical valve, the lasting requirement is the warfarin and the regular INR test that goes with it, often every few weeks. This man lived years with his valve doing its job. The clot in this case was not the valve failing. It was the protection around the valve being switched off for a few days.
(F) Are the newer valves better?
The technology has moved, though not in a way that erases the trade-off. Some newer mechanical valves, such as the On-X valve, are the subject of trials testing whether they can be managed with less anticoagulation, though warfarin is still required. (Canadian Journal of Cardiology 2020) On the tissue side, transcatheter aortic valve replacement, or TAVR, now lets some patients receive a valve through a catheter instead of open surgery, and the 2020 guidelines support it for many patients over 65. (JACC 2025) At seven years, a major low-risk trial found no difference in outcomes or valve durability between TAVR and surgery. (Healio 2025) But TAVR places a tissue valve, so the wear-out question still applies to younger patients, and a 2025 analysis found mechanical valves carried a survival advantage in patients 60 and under. (STS 2025) Newer does not mean free of the warfarin question. For a mechanical valve, that question never goes away.
(G) The price of durability meets a procedure
The same artificial surface that never wears out is also what activates clotting, and that is the trade a mechanical valve patient signs up for. (Harvard Health) About 13% of mechanical valve patients eventually need a noncardiac surgery or procedure, and each one forces the same decision: hold the warfarin, and if so, do you bridge the gap. (JTCVS 2018) Stopping warfarin before surgery is the point where that trade-off turns into a real decision.
(H) What the guidelines actually say about pausing the drug
The decision is not one-size-fits-all. The 2024 AHA/ACC perioperative guideline treats routine heparin bridging as potentially harmful for many patients because it raises bleeding risk, a Class 3 caution. But for patients at high thrombotic risk, including those with mechanical mitral valves and those with atrial fibrillation carrying added risk factors, bridging is reasonable, a Class 2a recommendation. (ACC 2024) The valve-specific guidance is similar: a bileaflet mechanical aortic valve with no other risk factor can be interrupted without bridging, but a mechanical valve with significant thromboembolic risk should have bridging considered when the INR drops below target. (2022 ACC/AHA Valve Guideline) This patient had a mechanical aortic valve plus atrial fibrillation. That combination puts him in the category where bridging is meant to be weighed, not skipped by default.
(I) Bridging is not a free fix, and the aPTT shows why
It would be easy to read this case as a simple lesson that bridging is always right. It is not that simple. Bridging with heparin raises the risk of perioperative bleeding by about 4% to 8%. (Balaji 2024) That bleeding risk is part of why a blood thinner gets paused before a procedure in the first place. And once heparin was running here, an aPTT came back far above target, which is over-anticoagulation and a bleeding hazard in its own right, corrected only after the dose was cut. Stop the drug and a clot forms. Run the drug too hard and bleeding follows. The work of periprocedural management is staying on the narrow path between those two, and that path is the hard part.
(J) Why INR 1.6 means something different on a mechanical valve
For ordinary atrial fibrillation, an INR target of 2.0 to 3.0 is standard. A mechanical aortic valve is held higher, at 2.5 to 3.5, because the artificial surface clots more readily than a native valve. An INR of 1.6 is well under that floor. It is the predictable result of three days without the drug. The number does not drop the moment the pill is skipped, and it does not climb back the moment it is restarted. That lag, measured in days at each end, is the window in which a clot has time to form.
(K) The mass nobody was looking for
The transesophageal study found a second, separate mass with the look of a myxoma or a fibroma. A cardiac myxoma is the most common primary tumor of the heart, though still rare, at roughly 0.5 to 1 case per million people each year, and most arise in the left atrium. (Cardiothoracic Surgeon 2024) These tumors are usually benign, but a meaningful share shed fragments that embolize, and a fragment that reaches the brain causes a stroke. Because of that, surgical removal is the standard once one is found. (StatPearls 2026) This is also where the value of the transesophageal echo shows up. A standard chest ultrasound is the first look, but the esophageal view defines the attachment point and checks for additional masses. Without that second study, the tumor here would likely have gone unseen. The test ordered to characterize a clot found a tumor instead.
(L) Why admission and transfer was the right call
A clinician could look at this man, stable and symptom-free, and wonder why he needs a hospital at all. The answer is the stack of findings rather than how he feels. He had an apical thrombus that could embolize, an INR too low to protect him, and an incidental cardiac mass that needs a surgeon’s eye. None of those can be managed safely from home. The plan was direct: start heparin immediately to cover the unprotected valve, restart warfarin, check INR daily, and transfer to a cardiothoracic center to evaluate the mass. Symptom-free does not mean low risk in this picture.
(M) What the trajectories show, and the decisions that move them
When a mechanical valve patient pauses anticoagulation without a clear bridging plan, the literature describes a recognizable set of outcomes: valve or chamber thrombus during the off-drug days, often silent until it embolizes; embolic stroke from a dislodged clot, which in mechanical valve thromboembolism carries roughly 20% mortality and 40% major disability (JTCVS 2018); and the opposite risk from over-correction, since bridging raises bleeding by 4% to 8% (Balaji 2024). If an incidental myxoma goes unaddressed, the embolic risk continues, while surgical removal is generally curative. Five decisions sit in the window after this admission, and they belong to the patient and the team.
- A written periprocedural anticoagulation plan agreed by both teams. The gap that caused this was no clear bridging decision between the specialists involved. A documented plan, owned by one named clinician, closes that gap.
- Bridging weighed against bleeding for each procedure individually. For a mechanical aortic valve plus atrial fibrillation, guidelines support considering bridging when the INR falls below target (ACC 2024).
- Surgical evaluation of the cardiac mass. If it is a myxoma, excision is the standard and is usually curative (StatPearls 2026).
- Early warfarin restart after any future procedure, resumed as soon as the patient can take it by mouth, to shorten the unprotected window.
- A single coordinating clinician for a patient under several specialists. The more doctors a patient sees, the more easily a medication decision falls into the space between them.
None of these are predictions for any one patient. They are the observed distribution. The curve is still open, and where a patient lands on it depends on how the next procedure is planned.
Two Costs, One Decision Window
| Clinical & Behavioral Scenarios | Estimated Facility Billing | Patient Out-of-Pocket (PPO) |
|---|---|---|
| (1) Actual: admission for apical thrombus, heparin bridge, and transfer for surgical evaluation | $28,000 to $55,000 | ~$8,500 (annual OOP max hit) |
| (2) Hypothetical: planned outpatient bridging for the procedure (heparin cover, monitored INR, no admission) | $400 to $1,200 (outpatient, per procedure) |
~$40 to $80 (copays only) |
| (3) Add: embolic stroke if the apical clot had dislodged | +$60,000 to $150,000 (acute + first-year rehab) |
OOP max re-hit + long-term disability |
| (4) Five-year: surgery for the mass plus repeated unplanned periprocedural events | +$150,000 to $400,000 | Annual OOP max + disability risk |
Sources: JTCVS 2018 (mechanical valve thromboembolism); ACC 2024 (perioperative anticoagulation). Facility and out-of-pocket figures are scenario estimates for a typical PPO and vary by plan and region.
For a PPO member who hits the annual out-of-pocket maximum in the same year either way, the dollar gap between an admission and a planned outpatient bridge narrows quickly. The variable that does not narrow is the stroke risk that sat in the unprotected window, and the time cost of an event that does not reverse. The admission treated one clot and started one bridge. What happens at the next procedure is decided by whether a plan is written before the warfarin is paused, not after.
The same pattern of a single daily medication and a single missed window shows up in the case of a man who stopped his blood pressure medication and arrived in heart failure. The same theme of a serious finding discovered while looking for something else runs through the multiple myeloma back pain case. And the cost of having no single clinician holding the whole picture appears again in the older men living alone case.
Tools for Reading Heart and Blood Numbers
A single lab value rarely tells the whole story. Three calculators that help frame heart and blood-panel numbers against age-matched references.
· Heart Age Calculator (Vascular Aging Predictor)
· Life Calculator (Cardiopulmonary Longevity Estimate)
· Blood Work Decoder (Cardiac & Metabolic Panel Reader)
Walt was stabilized over his admission. The heparin drip kept his blood thinned while warfarin rebuilt his INR toward the 2.5 to 3.5 range. His troponin stayed flat and his other numbers settled. The apical thrombus was managed medically rather than with any rushed intervention.
On the day of transfer, his wife followed the ambulance to the regional cardiothoracic center. The discharge summary listed the reason for transfer in one line: surgical evaluation of an intracardiac mass, with the apical thrombus bridged on heparin and warfarin resumed. He still felt the same as he had on the Wednesday his cardiologist found the clot on a screen.
The procedure that started all of this never happened. It moved to the back of a longer line, behind a clot and a mass that the preparation for it had brought to light. The next decision in front of Walt and his team is the mass. The decision behind it, the one that will repeat at every future procedure, is how to pause a blood thinner in a man whose valve cannot safely be left unprotected. This case does not show what every 76-year-old man should expect. It shows what stopping warfarin before surgery can surface in a mechanical valve patient, and why the plan matters as much as the pill.
This article is for general information and does not provide medical advice. The case described is a composite reconstructed from publicly reported clinical patterns and does not represent any specific patient. Anticoagulants such as warfarin should never be stopped, started, or adjusted on your own. Anyone with a mechanical heart valve who is facing a surgery or procedure should ask the prescribing physician how the blood thinner will be managed before, during, and after. New weakness, facial droop, difficulty speaking, or sudden vision changes should prompt an immediate emergency call.
Take care of yourself. Nobody else will do it for you.

Wilbur P is the editor of Manclub, leading coverage across health and life. His work is research-driven and built on primary sources a reader can verify – written for men in the second half of life who would rather know than believe. Based in Florida, still learning and still in the fight. Corrections, questions, story tips: [email protected].