
Hospital 366 Days · Case No. 40
The hospital’s year does not end at 365. It runs to 366, and keeps going.
Call him Stan. Age, location, and any potentially identifying facts have been changed. The clinical pattern is a composite reconstructed from cases hospitals see repeatedly, and it does not represent any specific patient.
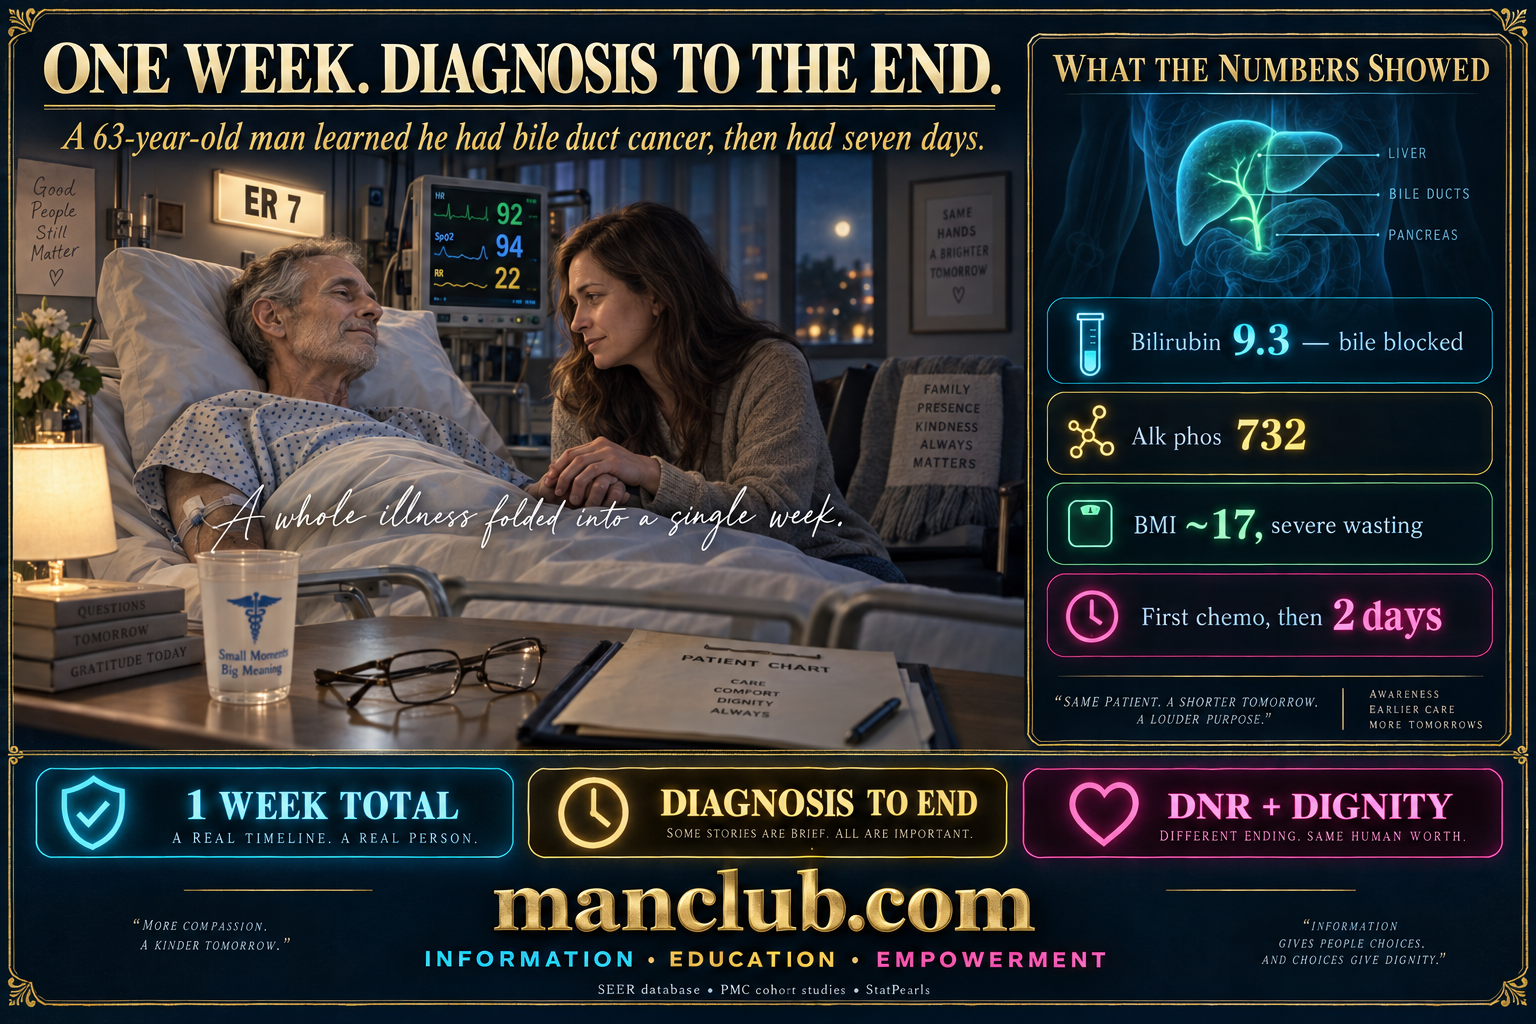
Stage 4 cholangiocarcinoma is a diagnosis that often arrives late and moves fast, and Stan’s case shows just how fast. One week before he came to the emergency room, he learned he had bile duct cancer. On the day he received his first round of chemotherapy, he was sent straight to the hospital. Two days after that, he was gone. This case file is about a week in which a diagnosis, a first treatment, an emergency visit, a hospice conversation, and a death all fell inside seven days.
Call him Stan. He was 63.
A week earlier he had been told he had cancer in the liver and the bile ducts. He said he did not know much more than that. He had been told, and the rest had not yet reached him.
For about a week his abdomen had felt full and swollen. He thought it was the liver, he said. Around midday, without much warning, came shortness of breath, a cough, and nausea. He had received his first chemotherapy session that same day, and from there he was sent to the emergency room. He denied alcohol. He denied a family history. He had stopped smoking.
The Week That Held Everything
The timeline is the case. A diagnosis one week old. A first infusion given that morning. An emergency room by the afternoon. It is a sequence that usually plays out over months, compressed here into days.
He came in short of breath, coughing, sick to his stomach. There was no home oxygen behind him, no clear picture he could give of what the cancer was doing. What he had was a body that had been quietly losing ground for longer than the week he knew about.
Who Stan Was Before Today
Stan’s frame told part of the story before the labs did. His body mass index was in the range that marks serious undernutrition, the wasting that advanced cancer brings as it pulls energy from the body faster than food can replace it. This is the state medicine calls cachexia, and it was well underway.
An imaging study from a month earlier had already described a liver largely taken over: massively enlarged, diffusely infiltrated, with a small amount of fluid around it. The disease had not appeared in the last week. Only the name for it had.
What the Admitting Team Found
The labs drew the shape of a blocked bile system and a stressed body.
The total bilirubin, a pigment the liver normally clears, was 9.3, several times what it should be. The alkaline phosphatase, an enzyme that climbs when the bile ducts are obstructed, was 732. Together those two numbers describe bile that cannot get out, backing up behind a tumor.
The liver enzymes were up as well, an AST of 142 and an ALT of 78, the sign of liver cells under injury. The white count was raised near 15.4, the platelets low at 112, the albumin down at 3.1, the magnesium low.
A chest film showed a collapsed segment of lung, an infiltrate, and a small amount of fluid on the right. The admitting diagnoses named pneumonia and a failure of the lungs to move enough oxygen, layered over the cancer underneath.
Reading the Clinical Markers
| Marker | Stan’s Value | Reading |
|---|---|---|
| Total bilirubin | 9.3 | Bile duct obstruction |
| Alkaline phosphatase | 732 | Blocked bile flow |
| AST / ALT | 142 / 78 | Liver cells injured |
| White cell count | 15.4 | Raised |
| Platelets | 112 | Low |
| Albumin | 3.1 | Low, poor reserve |
| Body mass index | ~17 | Severe undernutrition |
| Liver imaging | Enlarged, infiltrated | Advanced disease |
Two stories sit in this table. The bilirubin and the alkaline phosphatase are the tumor’s work, bile dammed behind a growth in the liver. The low albumin and the low body mass are the toll the disease had already taken on the body that had to carry it. One set names the cancer. The other names how little reserve was left to fight it.
Plain-Language Reference
| Term | What It Means in Plain Language |
|---|---|
| Cholangiocarcinoma | Cancer that begins in the bile ducts, the channels that carry bile from the liver. |
| Stage IV | Cancer that has spread beyond where it began, the most advanced stage. |
| Bile duct obstruction | A blockage that keeps bile from draining, so it backs up into the blood. |
| Bilirubin | A pigment the liver clears; it rises and yellows the skin when bile is blocked. |
| Alkaline phosphatase | An enzyme that climbs when the bile ducts are obstructed. |
| Hepatomegaly | An enlarged liver, here from tumor spreading through it. |
| Cachexia | The wasting of muscle and weight that advanced cancer drives. |
| Albumin | A blood protein that reflects nutrition over weeks; low values suggest depletion. |
| Goals of care | A conversation about what treatment a patient does and does not want near the end of life. |
| DNR | Do not resuscitate: an instruction not to attempt CPR if the heart stops. |
| Comfort care | Care aimed at easing symptoms rather than curing the disease. |
| Hospice | A model of care focused on comfort and dignity in the last phase of life. |
| Glycopyrrolate | A medicine used to reduce the airway secretions that cause noisy breathing at the end of life. |
| Terminal secretions | The rattling sound of fluid in the upper airway that can occur in the dying. |
From the Reviewer · Eleanor Hayes, M.D.
(A) A cancer that arrives late
In cases like this, the diagnosis often comes when the disease is already advanced. Cholangiocarcinoma grows in the bile ducts, where it can spread quietly before it produces symptoms a person notices. By the time the abdomen swells or the skin yellows, the tumor has usually been at work for some time. That is why so many patients in this pattern meet their diagnosis and their advanced stage in the same visit, with symptoms that stay quiet until the disease is far along.
(B) The numbers behind the jaundice
In cases like this, a bilirubin near ten alongside an alkaline phosphatase in the several hundreds describes one thing clearly: bile that cannot get out. A tumor in the liver presses on the ducts that should carry bile away, and it backs up into the blood. The rising liver enzymes add that the liver cells themselves are under injury. Read together, these numbers are the signature of a growth obstructing the bile system from inside the liver.
(C) What the timeline shows
In cases like this, the speed is not an anomaly so much as the disease at its most advanced. Metastatic bile duct cancer that goes untreated carries a published median survival measured in a few months rather than years, and across the broader metastatic group the median runs to roughly four to five months. For a patient already this depleted, the window narrows further. When a body has this little reserve, the time left is often measured in weeks, and sometimes in days.
(D) The first cycle lands hard on a depleted body
In cases like this, the first round of chemotherapy can be the hardest, especially for a patient already wasted by the disease. Treatment aimed at the tumor also taxes the body carrying it, and a frame this depleted has little to spare. The point is not that the treatment was wrong. It is that a body at this stage may have too little left to absorb even the intended cost of the care.
(E) Deciding while the mind is clear
In cases like this, the value of an early and honest conversation is hard to overstate. Stan was able to say, while his thinking was clear, that he wanted no resuscitation and a focus on dignity. That decision, made by the patient rather than left to others in a crisis, shaped everything that followed. Patients in this pattern who name their wishes early spare their families the burden of guessing under pressure.
(F) The sound families ask about
In cases like this, the noisy breathing that can come near the end, sometimes called terminal secretions, is often what worries families most. It is fluid moving in the upper airway, and it distresses the people listening more than it distresses the patient, who is usually beyond awareness of it. A medicine like glycopyrrolate is used to dry those secretions. It is chosen in part because it does not cross into the brain and add sedation, which matters when a patient is still awake and aware.
(G) The gap between being told and knowing
In cases like this, a patient who says he does not know much about his own diagnosis is describing something common and human. Being told a word is not the same as taking in what it means, especially in the compressed days between a diagnosis and a crisis. Part of the work near the end is closing that gap gently, so that decisions are made with understanding rather than only with information.
(H) A closing thought
In cases like this, a whole arc of illness can fold into a single week. A name for the disease, a first attempt to treat it, an emergency, a decision made in clarity, and a quiet end: all of it inside seven days. What the record holds is not a failure but a compression, the last stretch of a long illness arriving all at once. This series has sat with cancer that surfaced through other doors before, in a case of lung cancer that first showed as abdominal pain, and in a case of throat cancer tied to years of drinking and smoking.
What End-of-Life Care in Stage 4 Cholangiocarcinoma Costs, and Who Pays
Stage IV cholangiocarcinoma reaches the emergency room and the inpatient ward at the most expensive point in its course. A monitored bed, oxygen support, imaging, and the labs that mapped the blocked bile system all accrue across even a short admission.
The first chemotherapy session carries its own cost, and in a case like this it was given days before the end. That is one of the harder economics of advanced cancer: treatment aimed at extending life is at its most costly exactly when the time it can buy is shortest. The figures do not resolve into a clean answer, because the value of a first attempt cannot be read off a bill.
Hospice and comfort care shift the arithmetic rather than ending it. The goal changes from cure to comfort, and the spending follows, toward symptom relief rather than aggressive intervention. What this file only notes, rather than resolves, is that the largest cost here was never financial. It was measured in the days between a diagnosis and a death, and there is no line on any statement for that.
Tools for Reading Your Own Numbers
Two calculators that frame your own labs and longevity picture against age-matched references.
· Blood Work Decoder (Read Your Own Labs)
· Life Expectancy Calculator (Longevity Estimate)
This file closes with Stan’s pain eased, his wishes honored, and his family beside him. The hospital could do that part. When cure is off the table, comfort and dignity become the work, and they are work a ward can still do well.
The conclusion of this case is a single week that held a lifetime’s worth of turning points. A diagnosis, a treatment, a decision, and an ending, folded so close together that they nearly touched. The disease set that pace, not the people who cared for him. What they could offer at the end was not more time, but a gentler passage through the little that was left.
Names and identifying details in this case have been altered to protect privacy. The case is a composite reconstructed from publicly reported clinical patterns and does not represent any specific patient. This content is for general information only and is not medical advice, and reading it creates no provider-patient relationship. If you or someone close to you is facing an advanced cancer diagnosis, a conversation about goals of care, held early and while the mind is clear, is one of the most useful steps available.
Take care of yourself. Nobody else will do it for you.

Wilbur P is the editor of Manclub, leading coverage across health and life. His work is research-driven and built on primary sources a reader can verify – written for men in the second half of life who would rather know than believe. Based in Florida, still learning and still in the fight. Corrections, questions, story tips: [email protected].